
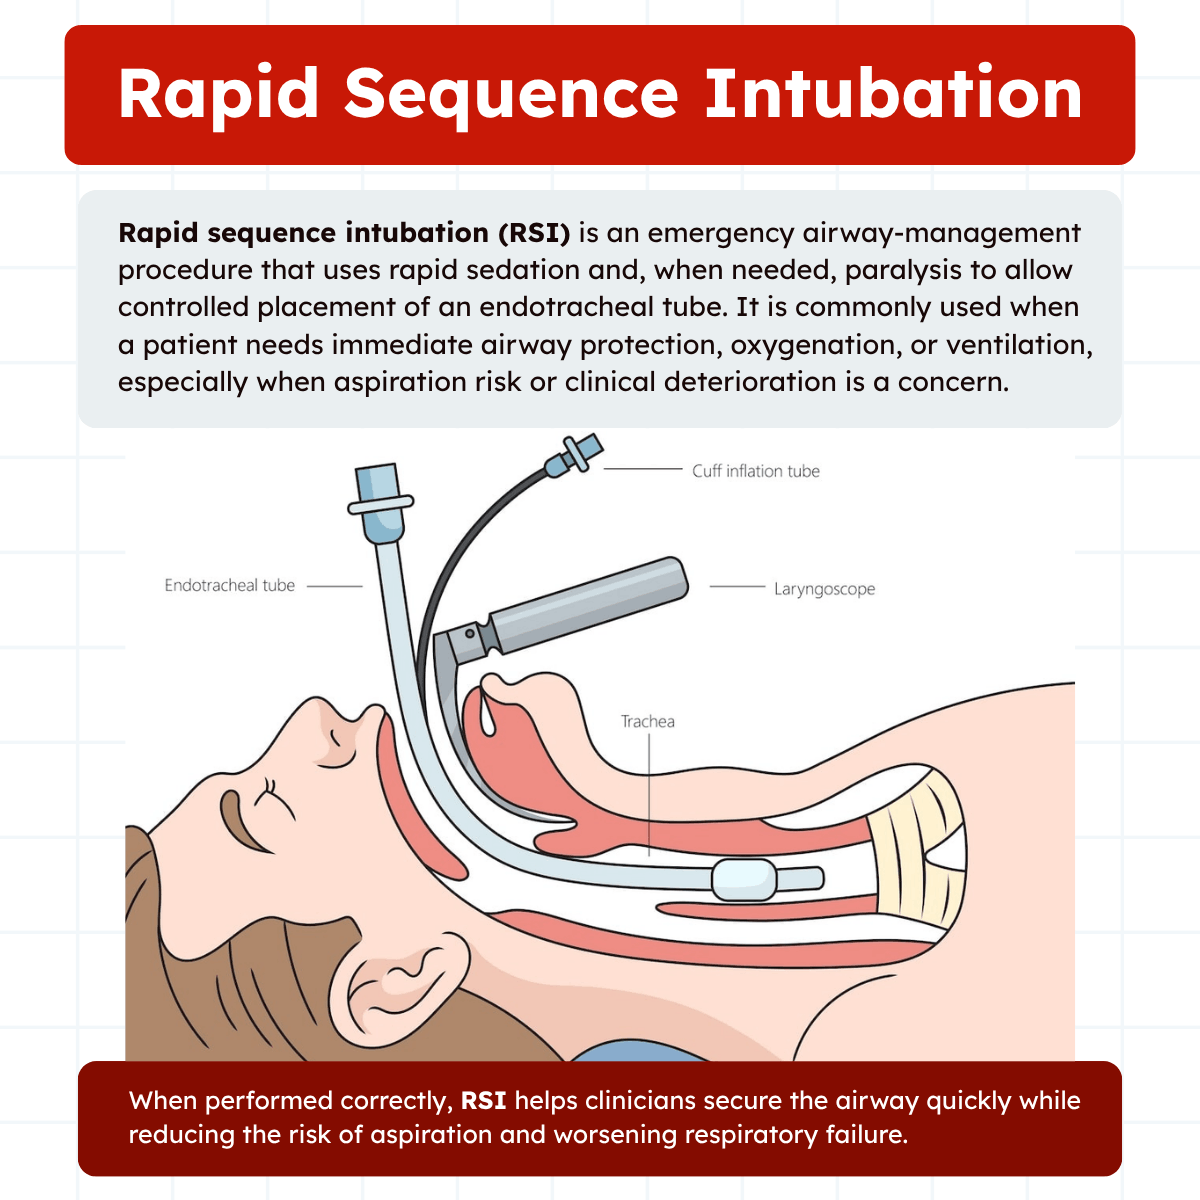
Rapid sequence intubation (RSI) is an emergency airway-management technique used when a patient needs rapid control of the airway. It involves giving medications to quickly produce unconsciousness and, when needed, muscle paralysis so an endotracheal tube can be placed safely and efficiently.
RSI is commonly used when a patient cannot maintain ventilation, oxygenation, or airway protection on their own.
Because the procedure can quickly remove the patient’s ability to breathe spontaneously, it requires careful preparation, proper equipment, skilled personnel, and a clear backup plan.

What Is Rapid Sequence Intubation?
Rapid sequence intubation is a controlled method of placing an endotracheal tube into the trachea under urgent conditions. The goal is to secure the airway quickly while reducing the risk of complications such as aspiration, hypoxemia, and failed airway control.
In respiratory care, RSI is important because it connects emergency airway management with mechanical ventilation. Once the endotracheal tube is placed, the patient often requires immediate ventilatory support. This means the procedure does not end when the tube passes through the vocal cords. The respiratory therapist and care team must confirm tube placement, secure the airway, provide oxygenation and ventilation, monitor the patient’s response, and make adjustments as needed.
RSI is not simply “fast intubation.” It is a structured process that includes patient assessment, preparation, preoxygenation, medication administration, intubation, tube confirmation, and post-intubation stabilization. Each step is designed to reduce risk during a high-stakes airway procedure.
Why Rapid Sequence Intubation Is Used
RSI is used when rapid airway control is necessary. This may occur when a patient cannot protect the airway, cannot ventilate adequately, cannot oxygenate adequately, or is clinically deteriorating.
Common indications include severe hypoxemia, airway obstruction, severe brain injury, abnormal respiratory frequency, hemodynamic instability, and high aspiration risk. A patient with altered mental status may lose the ability to protect the airway from secretions, vomit, or blood. A patient with severe respiratory failure may be unable to maintain adequate oxygen or carbon dioxide levels. A trauma patient may require airway protection before swelling, bleeding, or neurologic decline makes intubation more difficult.
RSI is also commonly used for conscious patients who have not fasted and are at high risk for aspiration. This is an important concept for board exams and clinical practice. A conscious patient may still have airway reflexes, stomach contents, anxiety, and resistance to airway manipulation. RSI allows the provider to rapidly induce unconsciousness and, if needed, paralysis so the tube can be placed quickly while minimizing prolonged bag-mask ventilation.
Manual ventilation before intubation can sometimes force air into the stomach, especially if excessive pressure is used. Gastric insufflation increases the risk of regurgitation and aspiration. For this reason, RSI is often designed to avoid unnecessary manual ventilation before the cuffed endotracheal tube is placed.
Goals of Rapid Sequence Intubation
The primary goal of RSI is to quickly secure the airway with an endotracheal tube. However, several additional goals are equally important.
- To support oxygenation. Patients who need RSI are often hypoxemic or at high risk of becoming hypoxemic during the procedure. Preoxygenation helps increase the oxygen reserve before apnea occurs.
- To support ventilation. A patient with respiratory failure may be unable to remove carbon dioxide effectively. Once the airway is secured, mechanical ventilation can be started to improve alveolar ventilation and gas exchange.
- To reduce aspiration risk. Many patients who require emergency intubation are not fasting, may have a full stomach, or may have impaired airway reflexes. RSI attempts to minimize the time between loss of consciousness and cuffed tube placement.
- To create better intubating conditions. Sedation and paralysis can reduce gagging, coughing, laryngospasm, resistance, and patient movement. This can make endotracheal tube placement faster and more controlled.
When RSI May Not Be Appropriate
RSI is not appropriate for every patient. If a patient can maintain adequate ventilation and oxygenation while breathing spontaneously, immediate RSI may expose the patient to unnecessary risk. In these cases, careful observation, noninvasive support, or a less urgent airway approach may be more appropriate.
RSI is also generally not used for unconscious patients who require immediate crash airway management. In a true crash airway situation, the patient may need immediate manual ventilation and intubation without waiting for anesthesia induction or paralysis. This distinction is important. RSI is used when there is enough time to prepare and give medications in a controlled sequence. A crash airway requires immediate action because the patient is already unconscious, apneic, or near arrest.
RSI should not be attempted by someone unfamiliar with the procedure, equipment, medications, or backup airway options. Once sedatives and paralytics are administered, the patient may become apneic and unable to protect the airway. If the provider cannot intubate or ventilate, the situation can rapidly become life-threatening.
Preparation Before RSI
Preparation is one of the most important parts of RSI. Once medication is given, the team has limited time to secure the airway. Every piece of equipment should be gathered, checked, and ready before induction.
Essential preparation includes a cardiac monitor, pulse oximeter, oxygen source, suction, intravenous access, bag-valve-mask device, advanced cardiovascular life support medications, and an appropriately sized endotracheal tube. A laryngoscope or video laryngoscope should be prepared, and the blade should be checked for proper function. A stylet, bougie, syringe for cuff inflation, tube-securing device, capnography, and backup airway equipment should also be available.
A cricothyrotomy tray or surgical airway equipment should be ready in case intubation fails and ventilation cannot be maintained. This preparation reflects the seriousness of RSI. The team must be ready for a “cannot intubate, cannot ventilate” emergency.
Note: The respiratory therapist may help prepare the equipment, check the endotracheal tube cuff for leaks, lubricate the tube, prepare suction, set up oxygen delivery, and ensure that ventilator equipment is ready after intubation.
Preoxygenation
Preoxygenation is performed before RSI to increase the oxygen reserve in the lungs. The goal is to replace nitrogen in the functional residual capacity with oxygen, giving the patient more time before oxygen saturation falls during apnea.
Preoxygenation is commonly performed with 100% oxygen. The patient’s oxygen saturation should be monitored continuously with pulse oximetry. However, clinicians must remember that pulse oximetry does not always provide a complete picture. For example, in carbon monoxide poisoning, pulse oximetry may appear falsely normal because many pulse oximeters cannot distinguish oxyhemoglobin from carboxyhemoglobin.
In critically ill patients, oxygen saturation can fall quickly even after preoxygenation. Patients with pneumonia, pulmonary edema, ARDS, severe asthma, obesity, pregnancy, or shock may have reduced oxygen reserves. These patients require especially careful planning because they may desaturate rapidly during laryngoscopy.
Medications Used in RSI
Medication use is central to RSI. The typical medication sequence includes an induction agent to produce unconsciousness and a neuromuscular blocking agent to produce paralysis.
- Etomidate is commonly used as an induction medication because it has a rapid onset and is often used in emergency airway management. It helps produce sedation and unconsciousness so the patient can tolerate laryngoscopy and intubation. A commonly referenced adult dose is 0.3 mg/kg IV, or approximately 20 mg IV, given over 30 to 60 seconds.
- Succinylcholine is a commonly used depolarizing neuromuscular blocker. It has a rapid onset, often around 30 to 60 seconds, and a relatively short duration, often around 8 to 10 minutes. A commonly referenced adult dose is 1 to 1.5 mg/kg IV, or approximately 100 mg IV.
- Rocuronium is a nondepolarizing neuromuscular blocker that may also be used for RSI. It is often considered when succinylcholine is contraindicated. Other medications may be used depending on the patient’s condition, including midazolam, fentanyl, lidocaine, and post-intubation sedatives or analgesics.
Note: Medication choice should be based on the patient’s clinical condition, the reason for intubation, hemodynamic status, neurologic concerns, and contraindications.
Important Medication Safety Points
One of the most important safety points in RSI is that paralytics do not provide sedation, amnesia, or pain control. A paralyzed patient may be unable to move, breathe, or communicate but may still be aware or in pain if sedation and analgesia are inadequate. For this reason, neuromuscular blockers must be paired with appropriate sedation, and analgesia should be considered when pain is present.
Sedatives also do not reliably provide pain control. They may reduce anxiety, produce amnesia, or cause unconsciousness, but they do not replace analgesics when the patient is experiencing pain. This is especially important after intubation, when the endotracheal tube, mechanical ventilation, trauma, procedures, or underlying disease may cause discomfort.
Succinylcholine has several important contraindications. It should be avoided in patients with a family history of malignant hyperthermia. It is also contraindicated in penetrating eye injury, hyperkalemia, chronic muscular conditions such as muscular dystrophy, and severe burns or crush injuries that are several days old. These conditions increase the risk of dangerous complications, including severe hyperkalemia.
Note: Because RSI medications have rapid onset, the clinician must be ready to intubate before they are administered. Giving sedatives or paralytics before equipment and personnel are prepared can create a dangerous delay in airway control.
Cricoid Pressure
Cricoid pressure, also called Sellick’s maneuver, has traditionally been used during RSI to reduce the risk of passive regurgitation and aspiration. The technique involves applying pressure to the cricoid cartilage to compress the esophagus.
The purpose is to help prevent stomach contents from entering the pharynx during the period between loss of consciousness and successful placement of the cuffed endotracheal tube. This aligns with one of the main goals of RSI, which is to protect the airway from aspiration.
However, cricoid pressure must be applied carefully. Excessive pressure can distort the airway, worsen the laryngoscopic view, or obstruct ventilation. If cricoid pressure makes intubation or ventilation more difficult, the team may need to adjust or release it. The key point is that cricoid pressure is not a simple automatic step. It requires proper technique, communication, and awareness of airway patency.
Intubation During RSI
Once unconsciousness and respiratory muscle relaxation are achieved, oral endotracheal intubation is performed. The provider visualizes the vocal cords and passes the endotracheal tube through the glottic opening into the trachea.
Direct visualization of the tube passing through the vocal cords is one of the most important ways to prevent esophageal intubation. If the vocal cords cannot be clearly seen or identified, the tube should not be blindly inserted. Instead, another experienced provider may need to attempt intubation, or alternative airway equipment may be required.
Difficult intubation can occur because of limited mouth opening, poor positioning, unusual airway anatomy, trauma, swelling, blood, secretions, or obesity. Special tools may be helpful, including video laryngoscopy, different laryngoscope blades, specialized stylets, and a bougie. A bougie can be passed through the glottic opening first, allowing the endotracheal tube to be advanced over it into the trachea.
The care team should avoid prolonged intubation attempts. Long attempts increase the risk of hypoxemia, bradycardia, aspiration, and cardiac arrest. If intubation is unsuccessful, oxygenation and ventilation must be restored, and the backup airway plan should be activated.
Confirming Tube Placement
Tube placement must be confirmed immediately after intubation. An unrecognized esophageal intubation can be fatal because the patient may receive no effective ventilation despite the appearance of airway management.
Initial confirmation includes observing chest rise, auscultating for bilateral breath sounds, listening over the epigastrium, checking oxygen saturation, and assessing the patient’s clinical response. However, clinical assessment alone is not enough.
Carbon dioxide detection is a key method for confirming tracheal placement. Colorimetric CO₂ detectors change color in the presence of exhaled carbon dioxide. A typical color change from purple to tan or yellow suggests that the tube is in the trachea. Continuous waveform capnography is especially useful because it provides ongoing evidence of ventilation.
However, carbon dioxide detection must be interpreted in context. During cardiac arrest, exhaled carbon dioxide may be very low because pulmonary blood flow is poor. This can produce a false-negative reading even when the tube is correctly placed. Once effective chest compressions improve blood flow to the lungs, end-tidal carbon dioxide should in